The U.S. Food and Drug Administration has approved a B-cell-targeted treatment to reduce relapses in people with a difficult form of nephrotic syndrome that begins in childhood.
The treatment, obinutuzumab, is now approved for adults and children aged 2 years and older with frequently relapsing or steroid-dependent, childhood-onset idiopathic nephrotic syndrome who are currently in remission.
That final point is important.
The approval is not for every person with nephrotic syndrome, and it is not intended simply to treat any episode of swelling or protein loss.
It applies to a specific group of patients whose disease repeatedly returns or requires ongoing steroid treatment and who have already achieved remission.
The approval was supported by the randomized Phase 3 INShore trial, which compared obinutuzumab with mycophenolate mofetil, an immunosuppressive treatment commonly used in this condition.
At one year, sustained complete remission was achieved by 95.5% of patients receiving obinutuzumab compared with 73.2% receiving mycophenolate mofetil.
What is idiopathic nephrotic syndrome?
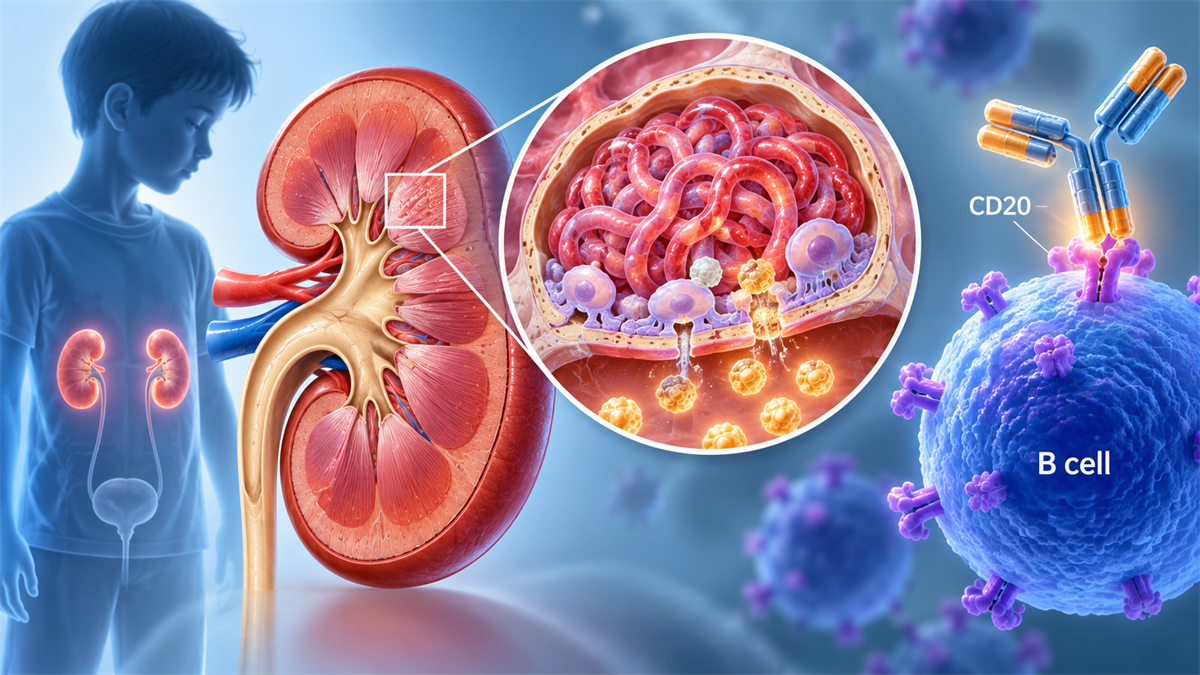
The kidneys contain millions of microscopic filtering structures called glomeruli.
Normally, these filters keep important proteins in the bloodstream while allowing waste products and excess water to pass into urine.
In nephrotic syndrome, the filtering barrier becomes abnormally leaky.
Large amounts of protein can then escape into the urine.
This can cause:
- very high urine protein levels;
- low albumin levels in the blood;
- swelling, particularly around the eyes, legs or abdomen;
- abnormal blood lipid levels;
- and an increased risk of complications such as infections and blood clots.
In many children, doctors cannot identify a specific underlying cause.
This is called idiopathic nephrotic syndrome.
Why are relapses a problem?
Many children initially respond well to corticosteroids.
The difficulty is that the disease may return.
Some patients experience frequent relapses, while others become steroid-dependent, meaning the disease repeatedly returns when steroid treatment is reduced or stopped.
Repeated or prolonged corticosteroid treatment can itself cause substantial problems, including effects on growth, bones, blood pressure, weight, blood sugar and infection risk.
Doctors therefore use other immune-suppressing medicines in patients with difficult relapsing disease to try to maintain remission while reducing steroid exposure.
Mycophenolate mofetil is one such treatment.
What is obinutuzumab?
Obinutuzumab is a monoclonal antibody directed against CD20, a protein found on B cells.
B cells are part of the immune system.
Abnormal immune activity involving B cells is thought to contribute to several immune-mediated kidney diseases.
By targeting CD20, obinutuzumab causes profound depletion of B cells.
The drug is not entirely new.
It has previously been used for certain blood cancers and has also been approved for active lupus nephritis.
What is new is its FDA-approved use in frequently relapsing or steroid-dependent childhood-onset idiopathic nephrotic syndrome.
What did the INShore trial test?
INShore was a randomized, controlled, open-label, multicentre Phase 3 study.
It enrolled 85 patients with childhood-onset frequently relapsing or steroid-dependent idiopathic nephrotic syndrome.
Participants were aged 2 years or older and had to be in complete remission when entering the study.
They were randomly assigned to receive either:
- intravenous obinutuzumab; or
- oral mycophenolate mofetil.
The main outcome examined whether patients could remain in sustained complete remission through one year.
What did the trial find?
At week 52:
- 95.5% of patients receiving obinutuzumab achieved sustained complete remission;
- compared with 73.2% receiving mycophenolate mofetil.
The adjusted difference was about 23 percentage points.
Other outcomes also favored obinutuzumab.
Patients receiving obinutuzumab had fewer relapses and lower cumulative glucocorticoid exposure during the trial.
These findings are clinically important because the goal of treatment is not simply to make urine protein disappear temporarily.
For patients whose disease repeatedly returns, maintaining remission while reducing repeated steroid treatment is a major objective.
Does this mean nephrotic syndrome has been cured?
No.
A sustained remission means the disease remains controlled without relapse during the measured period.
It does not prove that the underlying tendency to develop nephrotic syndrome has permanently disappeared.
Longer-term follow-up remains important.
What are the risks?
Obinutuzumab is a powerful immune therapy and its benefits need to be considered alongside significant risks.
The FDA label carries boxed warnings for:
- hepatitis B virus reactivation;
- and progressive multifocal leukoencephalopathy (PML), a rare but potentially devastating viral infection of the brain in immunocompromised people.
Common problems in patients with idiopathic nephrotic syndrome include infections, infusion-related reactions and neutropenia, which means a reduced number of infection-fighting white blood cells.
In the Phase 3 trial, adverse events were common in both treatment groups, and severe adverse events occurred more frequently in the obinutuzumab group than in the mycophenolate group.
These risks mean the treatment requires appropriate patient selection, screening and medical monitoring.
Who exactly received FDA approval?
The approved population should be described carefully.
Obinutuzumab is approved to reduce the risk of relapse in:
- adults and children aged 2 years and older;
- whose idiopathic nephrotic syndrome began in childhood;
- whose disease is frequently relapsing or steroid-dependent;
- and who are currently in remission.
The approval should not be generalized to all causes of nephrotic syndrome.
Nephrotic syndrome can result from many different kidney diseases, and those conditions may require very different treatments.
Why does this approval matter?
Childhood-onset idiopathic nephrotic syndrome can become a long-term cycle of remission, relapse and repeated immune-suppressing treatment.
The INShore trial provides randomized evidence that a B-cell-depleting strategy can maintain remission more effectively than mycophenolate mofetil during the measured period.
FDA approval now moves that strategy from an investigational approach into an authorized treatment option for the specified patient group in the United States.
It also reinforces a broader change occurring in kidney medicine: increasingly, treatments are being designed around specific immune mechanisms rather than relying only on broad immunosuppression.
For families affected by frequently relapsing or steroid-dependent childhood-onset nephrotic syndrome, the development provides another treatment option—but one that requires careful specialist supervision because of its substantial immune effects.